A Hedge Fund we work with asked, “Could Fentanyl be banned due to all the bad press it receives, like Quaaludes were banned?”
An Analyst who we’ve known since 1986 (yup, before the crash) had just read a report we wrote on Nutriband (NTRB) and its safer AVERSA abuse-deterrent fentanyl patch technology, and had a question. He brought up, “What are the chances of Fentanyl getting banned like Quaaludes did in 1984?”
Mic drop. And hmm… that’s a hair-raising question we hadn’t thought of. So we got in touch with another Biotech Analyst we work with (aka: share ideas over cocktails), and his verdict: Fentanyl won’t face the Quaalude fate.
If you ask most anyone what they think of Fentanyl, their opinion will be right up there with heroin—or using battery acid as toothpaste for a brighter, whiter smile! And it shouldn’t be like that, because illegal Fentanyl has grabbed the headlines, public commercials, and posters in an effort to save lives. So initially, there is a natural concern when hearing the name.
The fact is, for individuals enduring the agonizing, relentless grip of severe chronic pain – particularly those in advanced oncology or palliative care – the compound Fentanyl has been nothing short of a miracle.
Here is the “banned vs. not banned” dialogue, reformatted:
The Fentanyl Patch & Legal Prescriptions
- Annual Prescriptions: According to the Drug Enforcement Administration (DEA), legal prescriptions for pharmaceutical fentanyl in the United States were approximately 1.7 million prescriptions. One prescription = multiple patches.*
- Medical Context:
- Transdermal Patches (80%–90% of retail market): Used extensively for continuous, around-the-clock management of severe chronic pain (primarily in oncology and palliative care). They are designed to release medication slowly through the skin over a 48-to-72-hour period.
- Indication: Legal pharmaceutical fentanyl is a potent Schedule II synthetic opioid reserved strictly for severe chronic pain (such as in cancer care) or monitored surgical anesthesia.
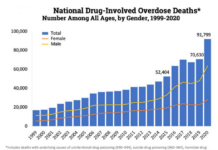
- Distinction from Illicit Fentanyl: The vast majority of fentanyl discussions center on illicitly manufactured fentanyl smuggled or distributed illegally, which drives tens of thousands of overdose deaths and is entirely separate from regulated medical supervision.
While aggregate prescription databases do not publish a singular daily percentage, comprehensive clinical utilization reviews indicate that transdermal patches represent the vast majority of outpatient legal fentanyl prescriptions, typically accounting for 80%–90% of the outpatient retail market.
Why the FDA Won’t Ban Legal Fentanyl
As for the FDA (whose staff also read the daily Fentanyl news) someday declaring that banning Fentanyl will be “good for the country and can save tens of thousands of lives” – our analyst just doesn’t see it happening.
Virtually all the negative news and public awareness stems from illicitly manufactured fentanyl, which is mixed into street drugs or pressed into counterfeit pills. Because the names are identical, it is very common for people to confuse the street crisis with regulated prescription drugs.
However, the FDA cannot and will not ban legal medical fentanyl simply as a public relations move or an act to “solve the problem.” The reason is rooted in how federal drug regulation works:
- Distinct Legal Channels: The FDA only regulates the legal pharmaceutical supply chain (manufacturers, pharmacies, and physicians). Banning medical fentanyl would entirely strip a critical tool away from doctors treating cancer patients, while doing absolutely nothing to stop cartels smuggling illicit chemical precursors across borders to make street fentanyl. Regulators are fully aware that stopping prescription patches will not change the illegal supply on the street.
- The Medical Necessity Threshold: By law, the FDA evaluates a drug based on its clinical benefit-to-risk ratio for patients. For individuals suffering from severe breakthrough cancer pain or those undergoing complex surgical procedures, medical fentanyl provides essential, localized relief that other drugs cannot match. Completely banning it would violate the FDA’s mandate to preserve access to effective medications for patients with legitimate medical needs.
- Strict Safety Control Over Banning: Instead of a total ban, the FDA manages high-risk medications using a system called REMS (Risk Evaluation and Mitigation Strategies). For example, the FDA’s TIRF REMS Program mandates that any doctor prescribing certain fast-acting fentanyl products—and any pharmacy dispensing them—must be specially certified and registered. This keeps the drug tightly controlled without a complete prohibition.
- What Law Enforcement Actually Bans: When you hear about the government banning fentanyl substances to fight the street crisis, they are usually referring to actions by Congress or the Drug Enforcement Administration (DEA) to permanently outlaw fentanyl analogues. For instance, legislation like the HALT Fentanyl Act was designed to permanently ban altered street variants (“fentanyl-related substances”) to ensure law enforcement has the authority to seize them. These bans explicitly exempt FDA-approved medical formulations used in hospitals.
Ultimately, the medical community and federal regulators maintain a strict wall between the criminal crisis of illicit street fentanyl and highly restricted medical treatments.
Act I: The Careless Guest (The Tale of Quaaludes)
In the 1970s, a drug named Quaalude entered the market. It was supposed to be a quiet, safe sedative to help people sleep. Instead, it threw a massive, uncontained party.
Because Quaaludes were standard oral pills, they were incredibly easy to abuse, pass around at discos, or divert to the street. The manufacturer, completely overwhelmed by negative press and corporate headaches, effectively threw its hands up and walked away from the drug. When the DEA realized the drug had a high potential for abuse and that safer alternative sleep aids existed, they didn’t just kick Quaaludes out—they demolished the entire room by reclassifying methaqualone as Schedule I. They shut down the global chemical supply because the drug had become completely unmanageable.
Act II: The Ironclad Guard (The Tale of Nutriband)
Now, enter the modern era. Fentanyl is already inside the fortress, heavily restricted because it is an incredibly potent, necessary tool for severe cancer pain. But current generic patches have a security flaw: abusers can chew, scrape, or manipulate them to extract the opioid all at once.
Instead of trying to ignore the problem like the makers of Quaaludes did, Nutriband designed a security guard for the patch. They created a proprietary technology called AVERSA™, which embeds “aversive agents” directly into the structure of the patch.
If a patient wears the AVERSA Fentanyl patch normally, the medication flows safely into the skin just as intended to relieve chronic pain. But if someone tries to abuse it—by chewing it, swallowing it, or chemically extracting the drug—the aversive agents are instantly triggered, making the experience highly unpleasant, ineffective, or impossible to tolerate.
Why Nutriband’s Patch Won’t Face the Quaalude Fate
The fundamental reasons the FDA won’t ban Nutriband’s abuse-deterrent patch the way they banned Quaaludes come down to three structural differences:
- Solving the Problem vs. Being the Problem: Quaaludes were banned because the pill was the root source of a massive street addiction crisis. Nutriband’s technology is being developed specifically to prevent the abuse, misuse, and accidental exposure of an existing clinical drug. The FDA actively encourages this type of innovation.
- Medical Necessity: The medical community easily replaced Quaaludes with alternative sleep aids. There is no easy, equivalent replacement for the profound, continuous pain relief that transdermal medical fentanyl offers to terminal oncology and palliative care patients.
- The Street Crisis is Already Separate: Today’s crisis is driven by illicit street powder mixed into fake pills, not by patients misusing clinical patches. Banning an abuse-deterrent medical patch would punish legitimate patients while doing zero to stop illegal cartel supply.
By adding an inseparable layer of safety to a necessary drug, Nutriband’s technology allows medical fentanyl to remain accessible to the patients who genuinely need it, while locking the door against those who want to misuse it.
Goodbye to Quaaludes: A Historical Look
Unlike modern drug crises driven by cartel-made street chemicals, Quaaludes (the brand name for methaqualone) were purely a product of the legitimate pharmaceutical industry. This made them uniquely vulnerable to government intervention.
The downfall happened in three distinct stages:
- Corporate Exhaustion: Originally marketed in the 1960s as a safe, non-addictive alternative to barbiturates, Quaaludes quickly exploded into a massive street and disco drug. By 1978, the drug’s reputation was so toxic that the original manufacturer, William H. Rorer, Inc., sold the rights to the Lemmon Company. Rorer famously stated that while Quaaludes accounted for only 2% of their sales, they created 98% of their corporate headaches. Lemmon stopped manufacturing them entirely by 1983 because doctors grew too terrified of the stigma to prescribe them.
- The International Chemical Chokehold: Even as American factories stopped making the pills, underground labs were buying bulk methaqualone powder from international chemical plants in Europe and Asia to press fake “714” pills for the black market. To fix this, a DEA official named Gene Haislip pioneered a new strategy: he traveled to countries like West Germany, Austria, Hungary, and China, convincing their governments to completely halt the production and export of bulk methaqualone. By choking off the raw chemical ingredients globally, the DEA effectively starved the black market.
- The Federal Schedule I Ban: In August 1984, President Ronald Reagan signed a congressional bill officially reclassifying methaqualone as a Schedule I controlled substance. This classification declared that the drug had a high potential for abuse and no accepted medical use, making the production, sale, or possession of Quaaludes completely illegal in the United States.
We have good memories—RIP.
Back-of-the-Napkin Math: Fentanyl Patches at $4.95
According to the DEA and IQVIA National Prescription Audit, approximately 1.7 million total fentanyl prescriptions are dispensed in the US annually. Because a single prescription usually covers a 30-day supply rather than a full year, the final calculation changes significantly depending on whether you are looking at total annual prescription fills or assuming 1.7 million continuous, full-year patients.
Since standard medical guidelines require changing a transdermal patch every 72 hours (3 days), a standard 30-day prescription contains 10 patches, while a full 1-year continuous regimen requires roughly 122 patches ($365 \div 3$).
| Metric | Scenario A: 1.7M Total Annual Fills (Standard 30-Day Scripts) | Scenario B: 1.7M Full-Year Patients (Continuous 1-Year Supply) |
| Base Unit Count | 1,700,000 prescriptions filled per year | 1,700,000 distinct patients |
| Patches per Unit | 10 patches per standard prescription | 122 patches per patient per year |
| Total Annual Patches | 17,000,000 patches | 206,833,333 patches |
| Price Per Patch | $4.95 | $4.95 |
| Estimated Gross Sales | $84,150,000.00 | $1,023,825,000.00 |
Key Mathematical Variables
- The “Less-Than-Perfect” Average: Real-world adherence reduces these numbers because some patients discontinue use, switch to other pain management therapies, or have their doses adjusted by their doctors.
- Insurance Discrepancies: While a baseline wholesale or retail generic price might average around $4.95, actual insurance plan cost-sharing structures and manufacturer discounts heavily sway net market revenues.
About Nutriband Inc.
Nutriband is primarily engaged in the development of a portfolio of transdermal pharmaceutical products. Our lead product under development is an abuse-deterrent fentanyl patch incorporating our AVERSA™ abuse-deterrent technology. AVERSA™ technology can be incorporated into any transdermal patch to prevent the abuse, misuse, diversion, and accidental exposure of drugs with abuse potential.
The Company’s website is www.nutriband.com.
About Nutriband Inc.
Nutriband is primarily engaged in the development of a portfolio of transdermal pharmaceutical products. Our lead product under development is an abuse-deterrent fentanyl patch incorporating our AVERSA™ abuse-deterrent technology. AVERSA™ technology can be incorporated into any transdermal patch to prevent the abuse, misuse, diversion, and accidental exposure of drugs with abuse potential.
The Company’s website is www.nutriband.com.
Forward-Looking Statements
Certain statements contained in this press release, including, without limitation, statements containing the words ‘’believes,” “anticipates,” “expects” and words of similar import, constitute “forward-looking statements” within the meaning of the Private Securities Litigation Reform Act of 1995. Such forward-looking statements involve both known and unknown risks and uncertainties. The Company’s actual results may differ materially from those anticipated in its forward-looking statements as a result of a number of factors, including those including the Company’s ability to develop its proposed abuse-deterrent fentanyl transdermal system and other proposed products, its ability to obtain patent protection for its abuse technology, its ability to obtain the necessary financing to develop products and conduct the necessary clinical testing, its ability to obtain Federal Food and Drug Administration approval to market any product it may develop in the United States and to obtain any other regulatory approval necessary to market any product in other countries, including countries in Europe, its ability to market any product it may develop, its ability to create, sustain, manage or forecast its growth; its ability to attract and retain key personnel; changes in the Company’s business strategy or development plans; competition; business disruptions; adverse publicity and international, national and local general economic and market conditions and risks generally associated with an undercapitalized developing company, as well as the risks contained under “Risk Factors” and “Management’s Discussion and Analysis of Financial Condition and Results of Operations” in the Company’s Form S-1, Forms 10-K’s and Forms 10-Q’s, and the Company’s other filings with the Securities and Exchange Commission. Except as required by applicable law, we undertake no obligation to revise or update any forward-looking statements to reflect any event or circumstance that may arise after the date hereof.
All opinions soley that of Institutional Analyst (IA) and have not been reviewed or approved by management. Any forward-looking statement made by IA herein speaks only as of the date on which it is made. Factors or events that could cause our actual results to differ may emerge from time to time, and it is not possible for us to predict all of them. We undertake no obligation to publicly update any forward-looking statement, whether as a result of new information, future developments or otherwise, except as may be required by law. NTRB is a client of Institutional Analyst, publisher of the Biotech Stock Review, which receives a monthly retainer of five-thousand dollars for ongoing progress reporting and news coverage.
NTRB, #NTRB